VIMS EHSVIMS EHS

Workplace accident investigation and root cause analysis (RCA): 5 Why, Ishikawa diagram and CAPA

Root Cause Analysis (RCA) is a structured way of answering why an event was possible — not only who made a mistake. Its aim is to find the gap in the system (procedure, inspection, training, work organisation) and remove it with a corrective action so a similar event does not happen again.

A guide for safety professionals, investigation teams, managers and quality departments: how post-accident investigation works, why near misses are worth investigating, how to run 5 Why and Ishikawa step by step and how to close the analysis with CAPA actions.

  • accident investigation
  • RCA
  • 5 Why
  • Ishikawa diagram
  • near miss
  • CAPA

Published: 2026-10-04 · Updated: 2026-10-04 · 14 min read · Varilo deployment team

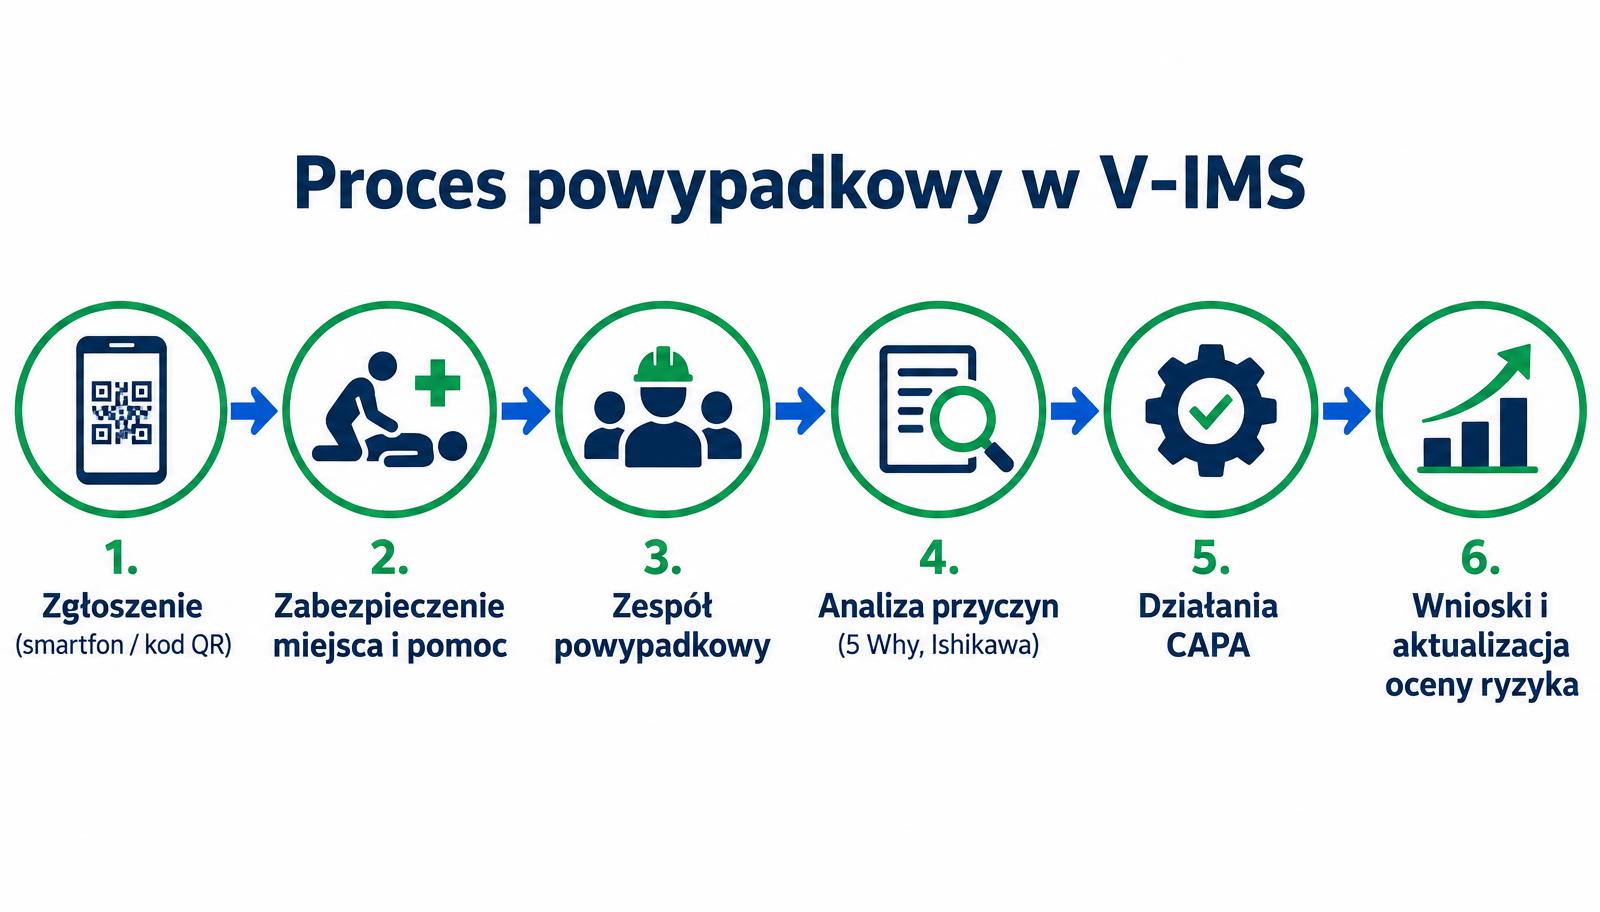
VIMS EHS — Six-step post-accident process: report, secure the scene, investigation team, root cause analysis, CAPA actions, risk assessment update
Six-step post-accident process: report, secure the scene, investigation team, root cause analysis, CAPA actions, risk assessment update

Why investigate accidents and incidents

An accident report is a legal duty, but its real value lies in the lessons. If an investigation ends with “the worker was not careful”, nothing changes — and the same situation returns with someone else.

A good investigation answers three questions: what happened, why it was possible and what we will change so it does not recur. The same logic applies to near misses, breakdowns, quality complaints and environmental incidents.

Post-accident procedure — the basics

After an accident, first aid and securing the scene come first, to prevent further injuries and preserve evidence. The employer then appoints an investigation team that establishes circumstances and causes and prepares a report — in Poland, as a rule, within 14 days of being notified of the accident.

The team inspects the scene, collects statements from the injured person and witnesses, gathers documentation (photos, sketches, instructions, inspection records, training, medical examinations) and proposes preventive measures. Always check current regulations for formal requirements — this guide is not legal advice.

Post-accident process in VIMS EHS: report via smartphone or QR code, securing the scene, investigation team, 5 Why and Ishikawa analysis, CAPA, lessons learned
From report to lessons learned: root cause analysis and CAPA are the steps most often missing in paper workflows. (Labels on the graphic are in Polish.)

Near misses: investigate before someone gets hurt

For every serious accident there are many minor injuries and even more near misses. They are the cheapest source of knowledge: nobody was hurt, people speak more openly and the causes are often the same as in serious events.

There is one condition — reporting must be simple and safe for the reporter. A QR code at the machine, a one-minute phone report, optional anonymity and feedback on what was done increase reporting more than any campaign.

The 5 Why method step by step

5 Why means asking “why?” until the answer points to a gap in the system rather than one person's behaviour. Five is a guideline — sometimes three questions are enough, sometimes seven are needed.

Rules: start from a concrete fact, not a judgement; confirm each answer with evidence (photo, record, interview); branch the analysis when several causes appear; stop when you reach a cause the organisation controls and can remove with an action that has an owner and a deadline.

The most common mistake is stopping at “human error”. Asking “why was the worker in a hurry?” usually leads to work planning, shift staffing or a missing instruction — and that is where the root cause lies.

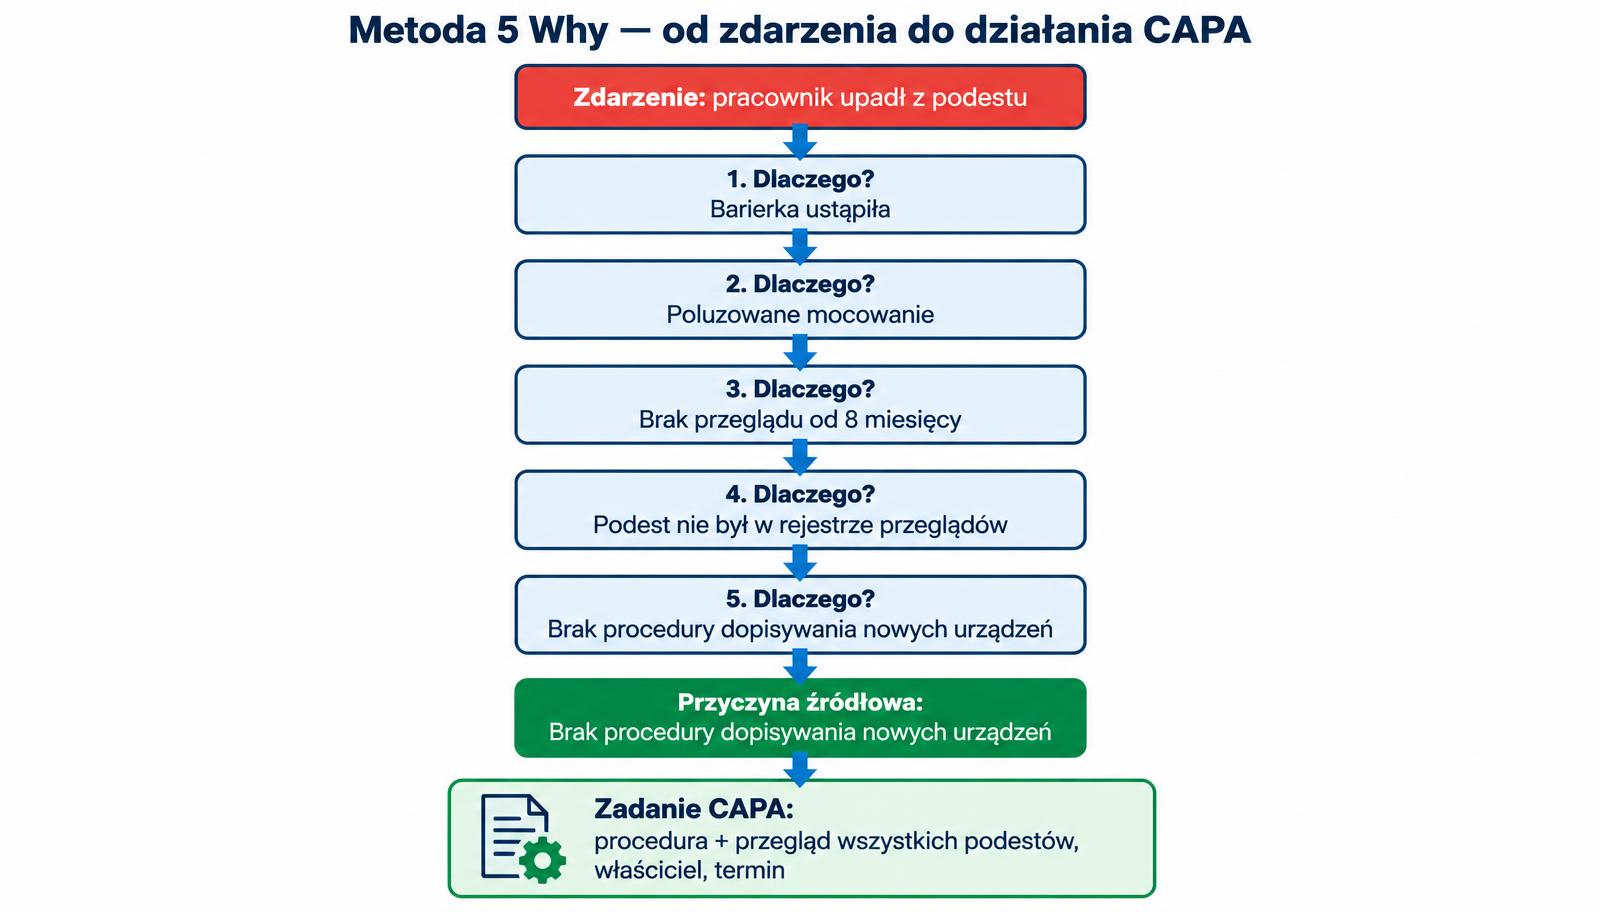
VIMS EHS — 5 Why example: fall from a platform, loose guardrail, no inspection, platform missing from inspection register, no procedure, CAPA task
5 Why example: from a fall from a platform to the root cause (no procedure for adding equipment to the register) and a CAPA task with owner and deadline. (Labels in Polish.)

The Ishikawa (fishbone, 5M) diagram

The Ishikawa diagram structures team brainstorming. The effect goes in the “fish head” and possible causes are grouped into categories: Man, Machine, Method, Material, Environment — often with a sixth category, Management or Measurement.

It works well when there may be many causes and the team needs a broad view before focusing on one hypothesis. Combining methods gives the best results: Ishikawa shows possible causes and 5 Why digs into the ones confirmed by evidence.

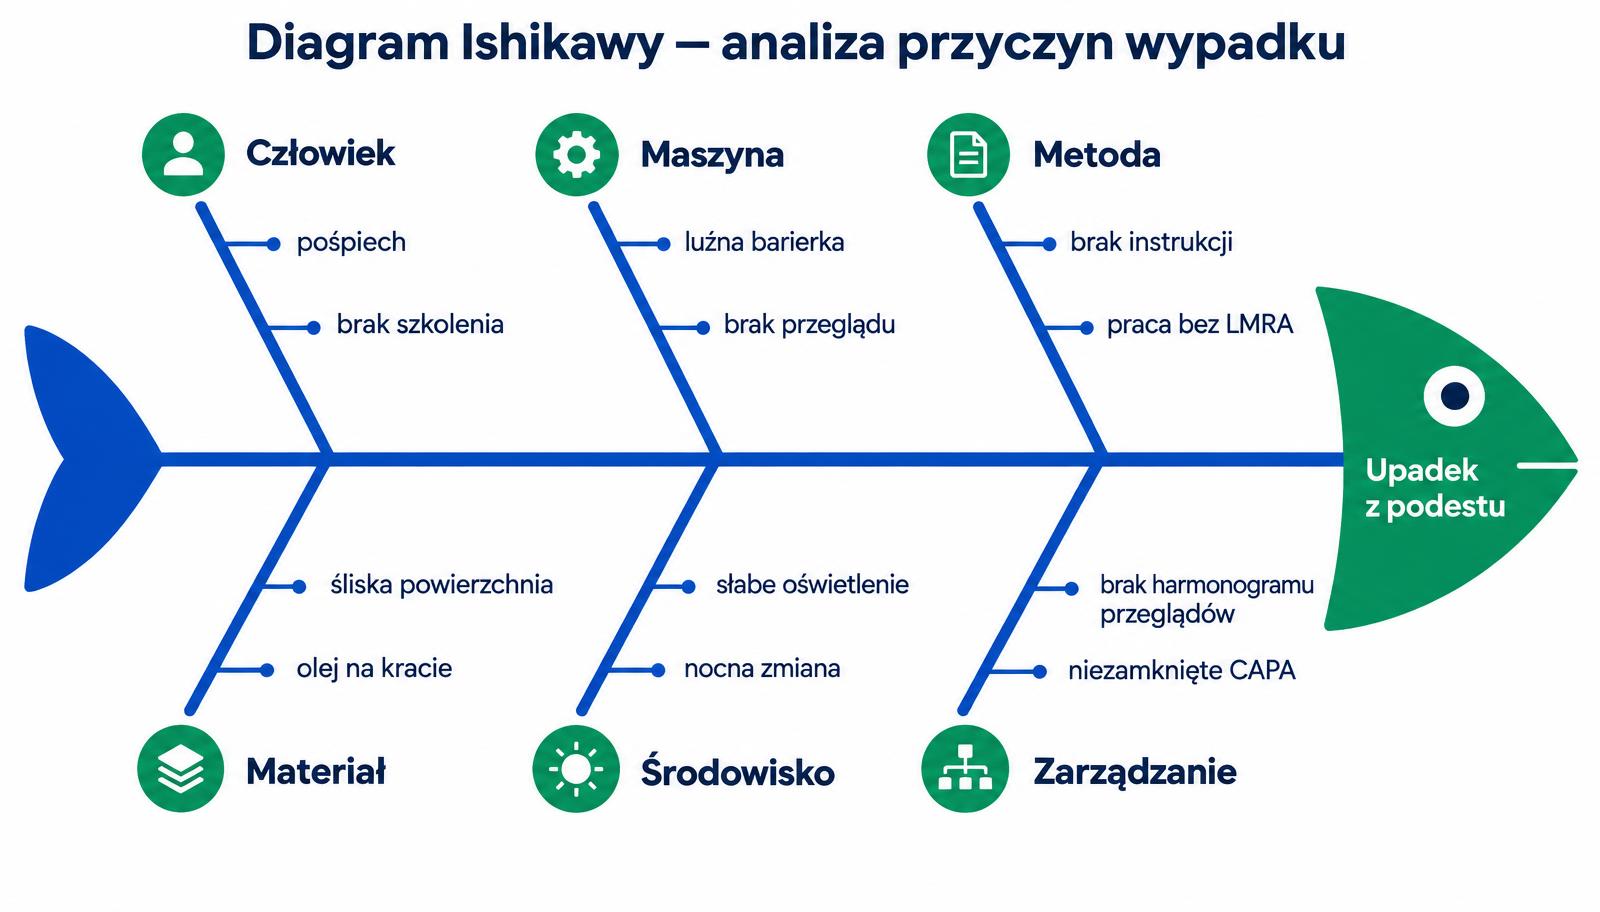
VIMS EHS — Ishikawa diagram for a fall from a platform with Man, Machine, Method, Material, Environment and Management categories
Ishikawa diagram for the same event: causes grouped into six categories help avoid missing organisational factors. (Labels in Polish.)

From cause to action: CAPA

An analysis without actions is just a document. Every confirmed root cause should have a corrective action (removes the cause) and, where it makes sense, a preventive one (applies the lesson to similar places, e.g. all platforms on site).

A good action has an owner, a deadline and an effectiveness criterion. After implementation, check that it worked and update the workstation risk assessment, instructions and training. The hierarchy of controls applies: elimination and engineering before administrative controls, PPE last.

Common mistakes in accident investigation

Looking for someone to blame instead of a cause; “instruct the worker” as the only action; no evidence for successive answers; investigating too late, when evidence is gone; actions without owner and deadline; no effectiveness check; ignoring near misses.

How VIMS supports accident investigation and RCA

In VIMS an incident or hazard report can be sent from a phone, including via a QR code, with photos and location. The accident and incident register follows the case from report through team documentation to close-out.

The root cause analysis module lets you run 5 Why and Ishikawa directly on the incident and turn conclusions into CAPA tasks with owner, deadline and effectiveness review. An incident can also flag that a workstation risk assessment needs review.

Glossary: workplace accident, investigation team, accident report and injury rates

Workplace accident — under Polish law (Act of 30 October 2002, Art. 3): a sudden event caused by an external factor, resulting in injury or death, connected with work. If any element is missing, the event is not a workplace accident.

Serious, fatal and multiple accidents — a serious accident causes grave bodily harm, a fatal one death within 6 months, a multiple one affects at least two people. The employer must notify the labour inspectorate and prosecutor without delay (Labour Code Art. 234 § 2).

Commuting accident — a separate category recorded on a commuting accident card, not in the workplace accident register.

Investigation team and accident report — the team (usually the OHS specialist and a worker representative) establishes circumstances and causes and issues the report within 14 days of notification. The accident is then entered in the accident register and a statistical card goes to Statistics Poland (Z-KW).

Technical, organisational and human causes — the classification used in reports and statistics. A human cause is rarely the root cause; it usually points to missing guarding, supervision or an unclear instruction.

Ishikawa 5M+E — diagram branches: man, machine, method, material, measurement and environment. They stop the team at the first obvious cause.

Heinrich and Bird pyramid — a model in which one serious accident sits on many minor injuries and hundreds of near misses. The ratios are illustrative, but the lesson holds: near miss reporting lets you act before injury.

Accident frequency rate and LTIFR — Statistics Poland reports injured persons per 1,000 employed; international reporting uses LTIFR, lost-time injuries per million hours worked.


Binder report vs digital incident register with RCA

Paper can meet formal duties — the difference is what happens to the lessons.

AreaBinder and spreadsheetsIncident register with RCA in VIMS
ReportingVerbal or on paper, often delayedPhone or QR code, photos and location immediately
Near missesRarely recordedSame simple form, optional anonymity
Cause analysisDescription in the report, no method5 Why and Ishikawa on the incident
ActionsList in the report, hard to trackCAPA tasks with owner, deadline and reminders
EffectivenessUsually not checkedVerified before the task is closed
TrendsManual summariesReports by location, cause and category

Key takeaways

  • The goal is to remove the cause, not to find someone to blame.
  • Near misses are the cheapest source of knowledge.
  • Combine methods: Ishikawa for breadth, 5 Why for depth.
  • Confirm every answer with evidence.
  • Every root cause needs an action with owner and deadline.
  • Check effectiveness and update the risk assessment.

Frequently asked questions

Who sits on the accident investigation team in Poland?

As a rule an OSH service employee and a social labour inspector — or, if there is none, an employee representative with up-to-date OSH training. In smaller firms the employer or an external specialist may act for the OSH service. Confirm the details of a specific case with a specialist.

When to use Ishikawa and when 5 Why?

Ishikawa for complex events with many possible causes, 5 Why for simpler chains. A combination of both usually works best.

Do near misses have to be investigated?

Employers should analyse hazards and events on site, and ISO 45001 explicitly requires incident investigation. In practice it is the best way to prevent accidents.

Who must be notified of a serious or fatal accident?

The employer must promptly notify the district labour inspector (PIP) and the public prosecutor of a fatal, serious or group accident, and secure the scene until the circumstances are established. Working through causes and CAPA is covered in our guide on the path from incident to risk assessment update.

How long is there to complete the accident report in Poland?

The investigation team issues the report no later than 14 days after being notified of the accident. Any delay must be explained in the report.

When must an accident be reported to the labour inspectorate and prosecutor?

Without delay when it is fatal, serious or multiple, and for any other accident with similar consequences.

What is the difference between a workplace and a commuting accident?

A workplace accident is connected with work and documented with an accident report and register entry. A commuting accident is recorded on a separate card and benefits follow different rules.

See incident investigation and RCA in VIMS

We will show how a phone report moves through 5 Why or Ishikawa analysis to CAPA tasks and a risk assessment update.